MALS treatment without surgery: options and limits
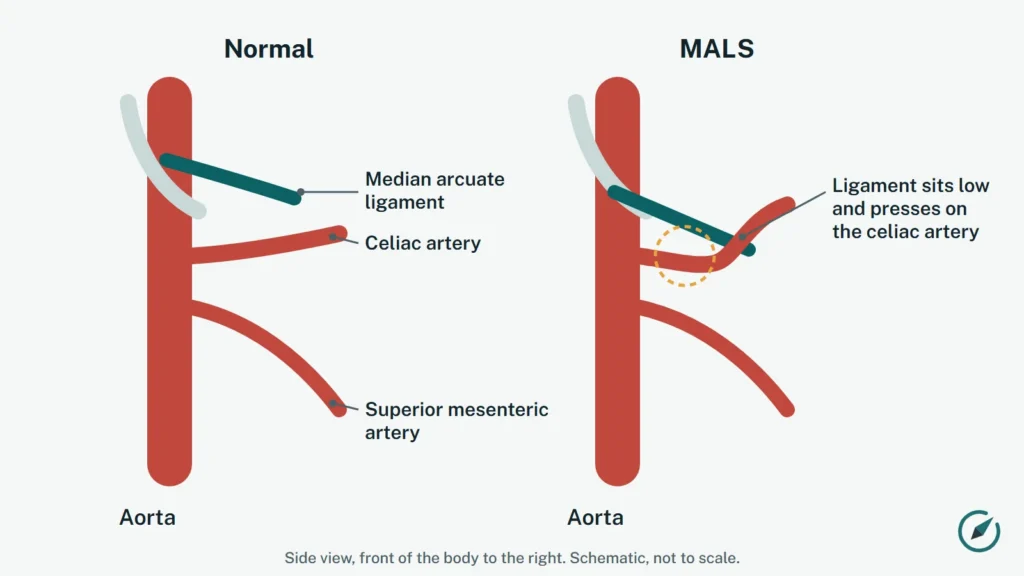
The standard treatment for median arcuate ligament syndrome (MALS) is an operation that releases the ligament pressing on the celiac artery. Many people still ask whether they can avoid surgery. The honest answer is that non-surgical care can help manage symptoms and plays an important role in deciding who should have surgery, but studies so far suggest that people treated without surgery tend to do worse [1][2].
Key points
- In one study, only 1 of 24 patients managed without surgery became symptom-free, and half had no change in symptoms [2].
- A celiac plexus block, an injection that temporarily blocks the nerves near the artery, is used to test whether pain is likely to respond to surgery [3][4].
- Whether surgery is always needed is still debated, because compression can be found in people without symptoms and long-term data are limited [1][8].
What non-surgical care includes
Non-surgical care usually means managing symptoms while the diagnosis is confirmed and other causes are ruled out. It can include pain management, treatment of nausea, attention to nutrition and weight, and support for the emotional strain of a long illness. These measures are aimed at symptoms and at keeping you as well as possible while decisions are made. Our page on eating with MALS covers nutrition.
Isolated case reports describe improvement without specific treatment, for example a patient who changed her diet with the help of a food diary and gradually gained weight [5]. Single cases cannot tell how often this happens.
How people do without surgery
The evidence on non-surgical management is small. In a study of 67 patients with chronic symptoms and confirmed celiac artery compression, 24 were managed without surgery and followed for about two years: 1 became symptom-free, 7 partly improved, 12 had no change and 4 got worse. In the same study, 43 patients who had surgery mostly improved [2]. A major review also concluded that patients treated without surgery appear to have worse outcomes [1].
These studies were not randomized: doctors chose who had surgery, so the groups may have differed in other ways. That is one reason the question is not settled.
Celiac plexus block: a test and a short-term treatment
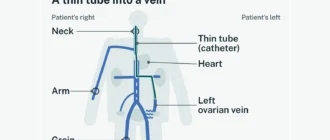
The celiac plexus is a network of nerves around the celiac artery. A celiac plexus block is an injection that temporarily blocks these nerves, guided by CT or fluoroscopy [3][6]. Many centers use it to see whether pain improves when these nerves are blocked:
- In 96 patients with a clinical diagnosis of MALS, postprandial pain decreased after the block in 84%, and nausea and vomiting became less common [3].
- In another study, 38 of 57 patients improved after the block; of those who then had surgery, 27 of 28 improved [4].
- An outpatient series reported a median pain reduction of 4 points on a numerical pain scale right after the block [6].
- In a large multi-center study, patients who had no relief from a celiac plexus block were more likely to have treatment failure after surgery [7].
The effect of a block is usually temporary [6]. Its main value is helping patients and doctors decide whether surgery is likely to help [7]. Read more about the nerve explanation of MALS on our neurogenic MALS page.
Is surgery always necessary?
Not everyone with a compressed celiac artery needs an operation. Compression is sometimes found on scans in people with no symptoms, and there are no agreed diagnostic criteria, so the diagnosis depends on careful evaluation [1][8]. Studies of outcomes after surgery mostly cover less than five years [1].
Some features seem to predict a better or worse response to surgery. In one study, pain after exertion predicted improvement, while vomiting and pain that came without a trigger predicted a poorer result [2]. In the large multi-center study, a history of gastroparesis and pain in many different places were linked to more treatment failures [7]. Your team can weigh these factors with you. See MALS surgery for the operation itself.
Questions to ask your doctor
- Which non-surgical treatments make sense for me while I am being evaluated?
- Would a celiac plexus block help decide whether surgery is right for me?
- Which of my symptoms make a good result from surgery more or less likely?
- What happens if I decide not to have surgery now?
Sources
- Goodall R, Langridge B, Onida S, et al. Median arcuate ligament syndrome. J Vasc Surg. 2020;71(6):2170-2176. PubMed 31882314
- Ho KKF, Walker P, Smithers BM, et al. Outcome predictors in median arcuate ligament syndrome. J Vasc Surg. 2017;65(6):1745-1752. PubMed 28189355
- Barbon DA, Hsu R, Noga J, et al. Clinical Response to Celiac Plexus Block Confirms the Neurogenic Etiology of Median Arcuate Ligament Syndrome. J Vasc Interv Radiol. 2021;32(7):1081-1087. PubMed 33862195
- Shnayder-Adams MM, Masotti M, Sanogo ML. Clinical Outcomes after Median Arcuate Ligament Release in Patients Responsive to Celiac Plexus Block. J Vasc Interv Radiol. 2024;35(4):558-562. PubMed 38181971
- Yoshida K, Kita K, Yamashiro S. A 56-year-old female with celiac artery compression syndrome recovering through dietary changes and weight gain. J Gen Fam Med. 2017;18(4):165-167. PubMed 29264017
- Bower KS, McCarthy CC, Vyasa P, et al. Celiac plexus block: A diagnostic tool for neurogenic median arcuate ligament syndrome. Pain Pract. 2025;25(1):e13403. PubMed 39099243
- DeCarlo C, Woo K, van Petersen AS, et al. Factors associated with successful median arcuate ligament release in an international, multi-institutional cohort. J Vasc Surg. 2023;77(2):567-577.e2. PubMed 36306935
- Petnys A, Puech-Leao P, Zerati AE, et al. Prevalence of signs of celiac axis compression by the median arcuate ligament on computed tomography angiography in asymptomatic patients. J Vasc Surg. 2018;68(6):1782-1787. PubMed 29914831
MALS Compass is an independent educational website, not a medical provider, and is not affiliated with any hospital, clinic or university. This page is educational information and does not replace advice from your own doctor. For any question about your health, please contact your doctor or an official healthcare institution.