Superior mesenteric artery (SMA) syndrome and how it differs from MALS
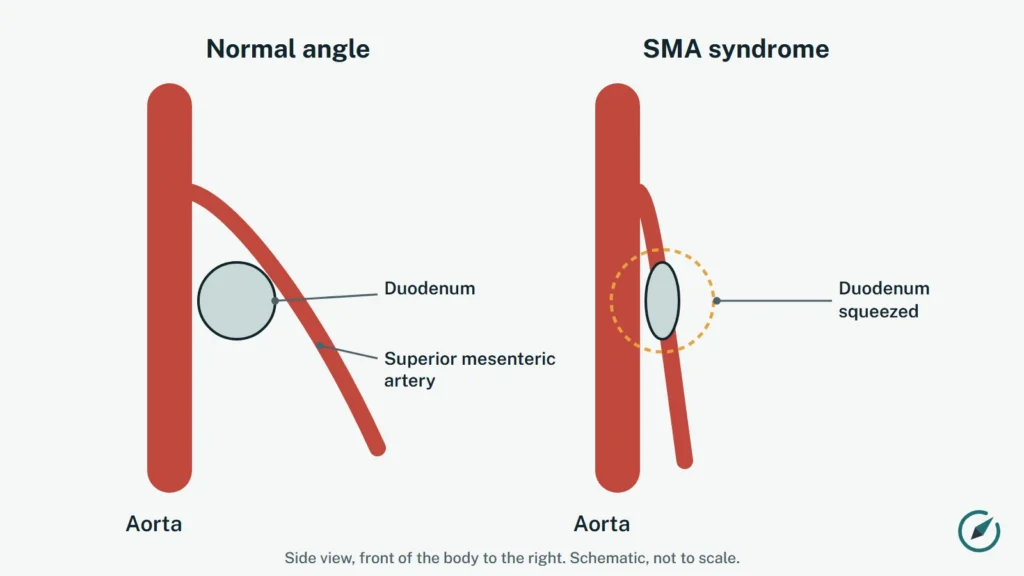
Superior mesenteric artery (SMA) syndrome is a rare condition in which part of the small intestine, the duodenum, is squeezed between two large blood vessels: the aorta behind it and the superior mesenteric artery in front of it. The squeeze blocks food from passing, which causes pain after eating, nausea, vomiting and weight loss [1][2].
Key points
- SMA syndrome is also called Wilkie syndrome, cast syndrome or aortomesenteric compression [1].
- It blocks the duodenum (part of the gut), while MALS compresses an artery, the celiac artery [1][6].
- CT scans can measure the angle and distance between the aorta and the SMA, which are smaller than normal in SMA syndrome [2].
- Treatment usually starts without surgery, with nutrition support; surgery is used when that does not work [1].
- SMA syndrome and MALS can occur in the same person, although this is rarely described [5].
What happens in the body
The superior mesenteric artery leaves the aorta at an angle and runs down in front of the third part of the duodenum. When the angle and the space become too small, the duodenum is pinched and its contents back up into the stomach [1][2].
A review of published cases reports a median age of 23 years, with the condition somewhat more common in women than in men (about 3 to 2) [1]. Weight loss is thought to play a role [5], and SMA syndrome is a recognized complication after spine surgery for scoliosis: in a review of 52 such cases most patients were teenage girls, and symptoms started on average about 10 days after the operation [4].
How SMA syndrome squeezes the duodenum (4 steps)

1. Normal anatomy. The superior mesenteric artery leaves the aorta at an angle. A pad of fat fills the space between the two vessels, and the third part of the duodenum crosses through it. Normal values are about 28 to 65 degrees for the angle and 10 to 34 mm for the distance. Source: study 1, study 2.

2. Weight loss shrinks the fat. After fast or large weight loss the fat pad shrinks. The angle between the artery and the aorta narrows and the distance between them gets shorter. In SMA syndrome the angle is typically under 22 degrees and the distance under 10 mm. Source: study 1, study 2.

3. The duodenum is squeezed. The duodenum is pinched between the artery and the aorta, so food has trouble passing. The stomach and the first part of the duodenum widen. Common symptoms are pain, nausea and vomiting after meals, early fullness and weight loss. Source: study 1, study 2.

4. Treatment: nutrition first. Treatment usually starts with nutrition, often through a feeding tube into the small bowel, to rebuild the fat pad. In one review, a modest weight gain of about 5.6 kg on average was linked with success. If this fails, surgery is used, most often a duodenojejunostomy bypass. Source: study 1, study 2, study 3.
Prefer a video? Watch the 90-second captioned video explainer.
Symptoms
The symptoms vary but often include [1]:
- abdominal pain after meals;
- nausea and vomiting;
- feeling full quickly (early satiety) and loss of appetite;
- weight loss.
Because these symptoms can look like an eating disorder or functional dyspepsia, the diagnosis can be missed. Repeated vomiting can cause serious problems such as changes in blood chemistry or inhaling vomit into the lungs, so an early diagnosis matters [1].
How SMA syndrome is diagnosed
CT scanning is the standard test. It shows a widened stomach and first part of the duodenum with a sudden narrowing where the duodenum passes between the aorta and the SMA [1][2]. On CT, doctors measure two things:
- the aortomesenteric angle: in one CT case series the patients had a mean angle of 13.5 degrees, compared with a normal range of 28 to 65 degrees;
- the aortomesenteric distance: a mean of 4.4 mm in the same patients, compared with a normal range of 10 to 34 mm [2].
Ultrasound is a safe extra option that can show in real time how the SMA moves and whether food passes through the duodenum [1]. An upper gastrointestinal X-ray study with contrast can show the blockage in the bowel itself [2].
SMA syndrome compared with MALS
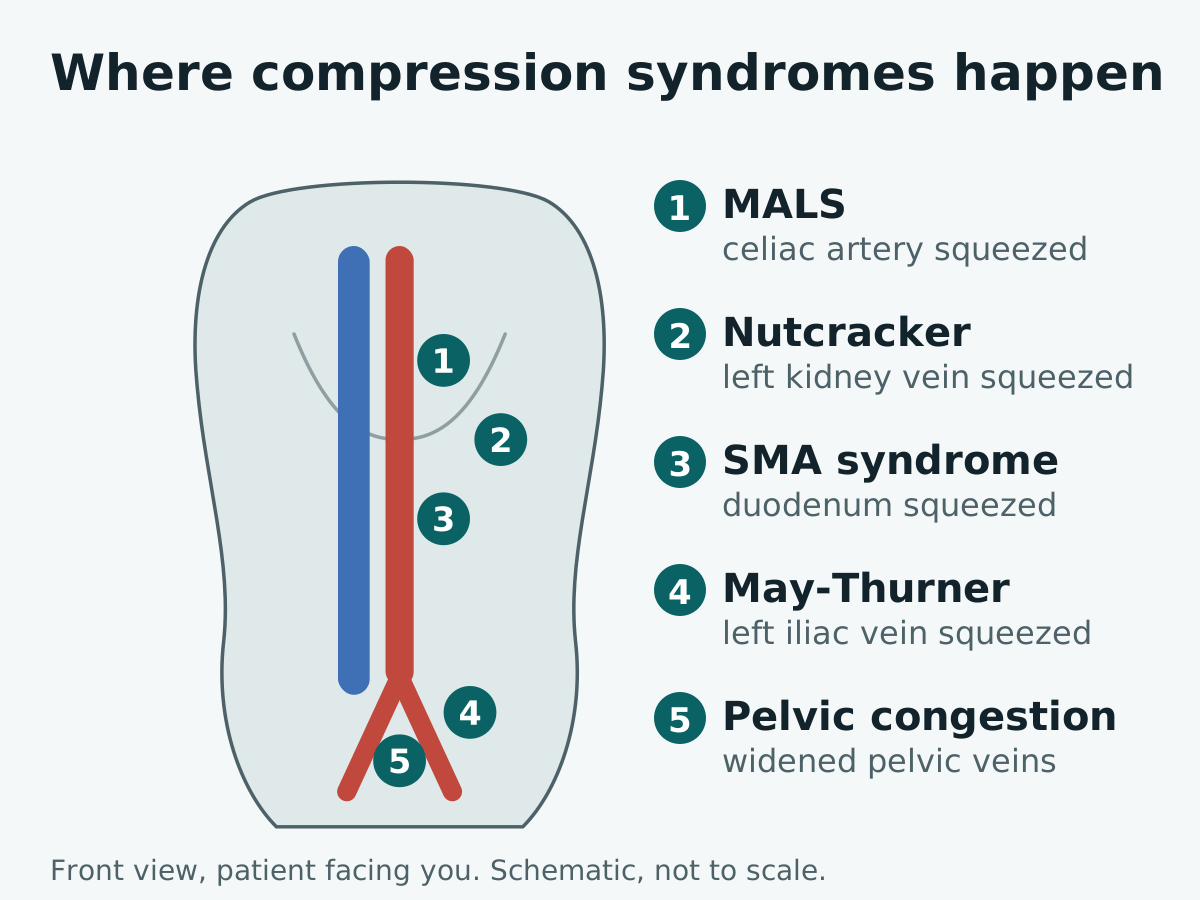
The two conditions are often confused because both cause pain after eating and weight loss. The difference is what is being compressed:
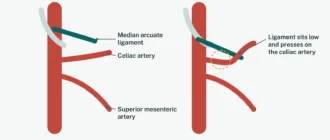
- MALS: the median arcuate ligament presses on the celiac artery, a blood vessel [6]. See What is MALS.
- SMA syndrome: the superior mesenteric artery and the aorta press on the duodenum, a part of the gut [1].
- Nutcracker syndrome: the same two arteries can also squeeze the left kidney vein [5]. See nutcracker syndrome.
These conditions can overlap. Doctors have described a patient with MALS, SMA syndrome and nutcracker syndrome at the same time; the authors suggested that weight loss caused by MALS pain may have helped trigger the other two [5]. A systematic review of surgery for both celiac artery compression and SMA syndrome found that symptoms persisted after the first operation in 28% of the celiac artery patients and 21% of the SMA syndrome patients, and stressed careful testing and patient selection before surgery [3].
Treatment
The first step is usually treatment without surgery: changing body position, emptying the stomach with a tube when needed, and nutrition support. Reported success rates for this approach are 70% to 80% [1].
When conservative treatment fails, surgery is recommended. The recommended operation is a duodenojejunostomy, which creates a bypass from the duodenum to the next part of the small intestine, by keyhole (laparoscopic) surgery. Reported success rates are 80% to 100% [1]. In the systematic review of surgical studies, major complications were reported in about 2% of SMA syndrome patients [3].
How well does treatment work? See results of surgery and nutrition from every published study: improvement rates by operation, recurrence and complications, side by side.
Read more: diet and nutrition in SMA syndrome and duodenojejunostomy and other operations.
Where is it treated? See US hospitals that publish on SMA syndrome, by state.
ICD-10 code
In the US ICD-10-CM 2026 code set, the index entry "Wilkie's syndrome" points to code K55.1 (chronic vascular disorders of intestine). Your doctor or insurer may also use codes for duodenal obstruction depending on the case.
Questions to ask your doctor
- Do my CT images show a small aortomesenteric angle and distance, and a widened stomach or duodenum?
- Could MALS or nutcracker syndrome be present as well?
- What is the plan for nutrition, and how will we measure if it is working?
- At what point would surgery be considered, and what type?
Current clinical studies
5 registered studies, 2 open or opening soon.
| Study | Status | Type / phase | Where | Last update |
|---|---|---|---|---|
| GT Metabolic Magnet System in Adults With Gastrointestinal Disorders |
Recruiting | Interventional | Canada | 2026-05-19 |
| Ultrasound Evaluation of Superior Mesenteric Artery Measurements in a Healthy Pediatric Population |
Recruiting | Observational | Switzerland | 2025-07-31 |
| Comparison of One Anastomisis Gastric Bypass and Duodeno-Jejunostomy for Treating SMA Syndrome |
Completed | Interventional | Egypt | 2025-12-08 |
| Fluoxetine in Refractory Superior Mesenteric Artery Syndrome by Targeting Comorbid Somatic Symptom Disorder |
Completed | Interventional | China | 2025-08-14 |
| SMAS: a Prospective Study in a Single Institution |
Completed | Interventional | Italy | 2018-01-31 |
Source: ClinicalTrials.gov (U.S. National Library of Medicine), checked November 18, 2026. Status is shown as reported by the registry. A listing is not an endorsement and does not mean a study is right for you: read the official record and discuss it with your doctor.
See all conditions on our clinical trials tracker.
Sources
- Oka A, Awoniyi M, Hasegawa N, et al. Superior mesenteric artery syndrome: Diagnosis and management. World J Clin Cases. 2023;11(15):3369-3384. PubMed 37383896
- Agrawal GA, Johnson PT, Fishman EK. Multidetector row CT of superior mesenteric artery syndrome. J Clin Gastroenterol. 2007;41(1):62-5. PubMed 17198067
- Jonas JP, Rossler F, Ghafoor S, et al. Surgical therapy of celiac axis and superior mesenteric artery syndrome. Langenbecks Arch Surg. 2023;408(1):59. PubMed 36690823
- Fan Y, Cai M, Wang J, et al. Superior Mesenteric Artery Syndrome Following Scoliosis Surgery: A Systematic Review of Case Reports. Ann Vasc Surg. 2021;76:514-535. PubMed 33905850
- Farina R, Gozzo C, Foti PV, et al. A man with the rare simultaneous combination of three abdominal vascular compression syndromes: median arcuate ligament syndrome, superior mesenteric artery syndrome, and nutcracker syndrome. Radiol Case Rep. 2021;16(6):1264-1270. PubMed 33854661
- Goodall R, Langridge B, Onida S, et al. Median arcuate ligament syndrome. J Vasc Surg. 2020;71(6):2170-2176. PubMed 31882314
MALS Compass is an independent educational website, not a medical provider, and is not affiliated with any hospital, clinic or university. This page is educational information and does not replace advice from your own doctor. For any question about your health, please contact your doctor or an official healthcare institution.