MALS in children and teens
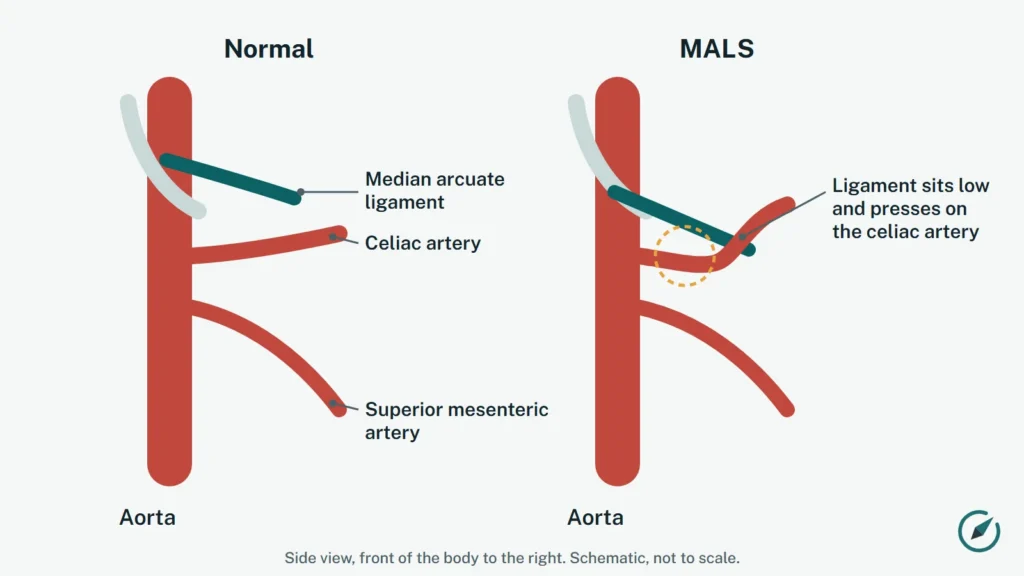
Median arcuate ligament syndrome (MALS) is diagnosed in children and teenagers as well as adults; in pediatric studies most patients were teenage girls with long-lasting abdominal pain [2][3][4]. Research in young patients is limited, and doctors still lack agreed diagnostic criteria and normal values for children [1].
Key points
- Typical symptoms in young people are abdominal pain, nausea, vomiting, food aversion and weight loss [1].
- Compression of the celiac artery can be found in children who have no pain; in one study only 57% of children with the finding had abdominal pain [2].
- POTS, hypermobile Ehlers-Danlos syndrome, anxiety and depression are common in young people diagnosed with MALS [1][3][4].
- Small studies report less pain and better quality of life after surgery, but other conditions can keep causing symptoms [3][5][6].
- Experts recommend care by a multidisciplinary team [1][3].
Symptoms in children and teens
A 2025 review of pediatric MALS describes abdominal pain, nausea, vomiting, diarrhea, aversion to eating and weight loss as the usual complaints [1]. Many young patients have had symptoms for a long time before the diagnosis; in one small surgical study the average was about 16 months [5].
The same symptoms are common in other childhood conditions, including reflux, irritable bowel syndrome, inflammatory bowel disease and gastroparesis, and these can occur alongside MALS. This overlap is one reason the diagnosis is difficult [1].
Why the diagnosis is harder in young people
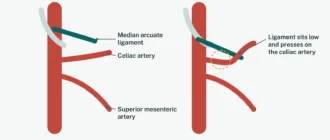
Doctors usually look for a narrowed celiac artery on duplex ultrasound and CT angiography [7]. In children, the finding alone says little:
- In a review of 82 children whose celiac artery compression was noticed during routine heart ultrasound, 57% had abdominal pain and the rest did not. Age, sex, weight and the measured blood flow speed did not predict who had pain [2].
- Children with joint hypermobility or symptoms of orthostatic intolerance (such as POTS) were more likely to have abdominal pain [2].
There are no agreed normal values for children, so results have to be interpreted together with the symptoms and after other causes are ruled out [1][7]. Our page on how MALS is diagnosed explains the tests.
Conditions that often come with MALS
In a group of 12 teenagers treated with robotic surgery, 83% had depression or anxiety, half had POTS, half had reflux and 42% had hypermobile Ehlers-Danlos syndrome; a third had another vascular compression syndrome [3]. In another study of 32 young patients, about half had a psychological condition before and after surgery [4].
These conditions do not mean the pain is "in the head". They matter because they can cause symptoms of their own, and treating them can be part of getting better [3].
Treatment and results
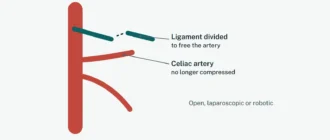
Surgery to release the ligament, usually by keyhole (laparoscopic) or robotic surgery, is the main treatment discussed in pediatric studies [6][7]. What the studies report:
- A systematic review found six pediatric studies with 195 patients; half of them reported symptom relief in more than 70% of patients, and four reported better quality of life. Most studies had a high or unclear risk of bias [6].
- In 6 patients followed before and after laparoscopic release, both the children and their parents reported better physical functioning and mental health afterwards [5].
- In 32 young patients, pain and quality of life improved six months after surgery. How children coped with pain before surgery, as seen by their parents (catastrophizing or feeling helpless), was linked to how much quality of life changed afterwards, which suggests psychological support before surgery may help [4].
- In the 12 teenagers treated robotically, MALS pain improved in 83%, but many still had symptoms from other conditions such as POTS or slow bowel movement [3].
Recovery after the operation is described on our page about recovery after MALS surgery.
Questions to ask your child's doctor
- Which other causes of my child's symptoms have been checked?
- How confident are you that the artery compression explains the pain, given that many children have it without symptoms?
- Should my child be evaluated for POTS, hypermobility or other conditions before surgery?
- Who will be on the care team, including psychological support and nutrition?
- How many children with MALS has your team treated, and how do you follow them up?
Sources
- Mostamand S. Median arcuate ligament syndrome: challenges, comorbidities, and controversies. Curr Opin Pediatr. 2025;37(5):447-451. PubMed 40904246
- Kakavand B, Burns RC, Centner A, et al. Median Arcuate Ligament Syndrome in Children: A Single-Center Experience. Cureus. 2024;16(3):e57184. PubMed 38681309
- DeCicco J, Raja F, Ganesan S, et al. Pediatric Outcomes After Robotic Median Arcuate Ligament Release, Celiac Ganglionectomy, and Lymphadenectomy. J Pediatr Surg. 2024;59(12):161664. PubMed 39209688
- Stiles-Shields C, Skelly CL, Mak GZ, et al. Psychological Factors and Outcomes in the Surgical Treatment of Pediatric Patients With Median Arcuate Ligament Syndrome. J Pediatr Gastroenterol Nutr. 2018;66(6):866-871. PubMed 29373439
- Joyce DD, Antiel RM, Oderich G, et al. Pediatric median arcuate ligament syndrome: surgical outcomes and quality of life. J Laparoendosc Adv Surg Tech A. 2014;24(2):104-10. PubMed 24328507
- Metz FM, Blauw JTM, Brusse-Keizer M, et al. Systematic Review of the Efficacy of Treatment for Median Arcuate Ligament Syndrome. Eur J Vasc Endovasc Surg. 2022;64(6):720-732. PubMed 36075541
- Skelly CL, Mak GZ. Median arcuate ligament syndrome - Current state of management. Semin Pediatr Surg. 2021;30(6):151129. PubMed 34930594
MALS Compass is an independent educational website, not a medical provider, and is not affiliated with any hospital, clinic or university. This page is educational information and does not replace advice from your own doctor. For any question about your health, please contact your doctor or an official healthcare institution.